








Paragraph 1: Confirmation and Immediate Response
Health officials in Jackson County, Missouri, have officially confirmed a case of measles, marking a critical juncture in the region’s public health landscape and prompting an immediate, multi-agency emergency response. The case, which was announced late this week by the county’s Public Health Department, was identified in an individual whose age and exact vaccination history have been kept confidential due to privacy regulations, though preliminary reports suggest the patient had not received the recommended MMR (Measles, Mumps, and Rubella) vaccine. The patient presented at a local urgent care facility with classic prodromal symptoms—high fever, persistent cough, coryza (runny nose), and conjunctivitis—followed by the distinctive maculopapular rash that typically begins on the face and spreads downward. Laboratory PCR testing confirmed the diagnosis, and the patient has been placed in strict isolation to prevent further transmission. The confirmation has triggered an exhaustive contact tracing operation, as measles is one of the most contagious infectious diseases known to medicine, with a basic reproduction number (R0) of 12 to 18, meaning a single infected individual can potentially infect up to 18 unvaccinated people. Health officials are currently working backwards to identify all locations the patient visited during the communicable period, including grocery stores, pharmacies, and a public library, warning that anyone who visited these specific venues during the designated time windows may have been exposed. The urgency of this notification is paramount, as the measles virus can survive for up to two hours in the airspace and on surfaces where the infected individual has coughed or sneezed, making casual contact in enclosed spaces a significant transmission risk.
Paragraph 2: The Epidemiological Context and Declining Vaccination Rates
The emergence of this measles case in Jackson County is not an isolated medical anomaly but rather a direct consequence of a dangerous epidemiological trend that public health experts have been monitoring with increasing alarm for over a decade. Medical professionals and county epidemiologists point to a steady and worrying decline in routine childhood vaccination rates across the state and the broader Kansas City metropolitan area, with the MMR vaccine coverage currently hovering around 88 to 90 percent—a figure that falls well below the 95 percent herd immunity threshold required to effectively interrupt the chain of transmission within a community. Jackson County has recorded a notable rise in conscientious exemptions for school-entry vaccinations, rising from 2.4 percent in 2018 to over 6 percent in the current academic year, a trend mirrored in surrounding suburbs and rural districts. This increasing cluster of unvaccinated individuals creates a fertile breeding ground for pathogens that were virtually eliminated from the United States in 2000, when measles was declared eradicated. The current case is likely the tip of the iceberg, as health officials confess that the patient may have exposed dozens, potentially hundreds, of individuals before the diagnosis was confirmed. Experts emphasize that the loss of herd immunity disproportionately impacts the most vulnerable populations—infants under twelve months who are too young for vaccination, immunocompromised individuals undergoing chemotherapy, and those with severe allergic reactions to vaccine components—all of whom rely on the collective immunity of the surrounding community for protection. The recent national uptick in measles cases, including a multi-state outbreak linked to international travel earlier this year, has placed local health departments on high alert, and this Jackson County case serves as a stark reminder that vaccination is not merely a personal choice but a civic responsibility that directly impacts public health safety nets.
Paragraph 3: The Specific Role of Vaccine Misinformation
In their official statements regarding the confirmed case, Jackson County health officials have been unequivocal in their assertion that the primary driver behind the vaccination gaps—and thus the current outbreak—is the pervasive and dangerous spread of vaccine misinformation. The county’s chief medical officer cited a litany of false narratives circulating on social media platforms, local community groups, and even some alternative health forums, which have systematically eroded public trust in the safety and efficacy of the MMR vaccine. Central to this misinformation campaign is the long-debunked claim linking the vaccine to autism, a hypothesis originating from a fraudulent 1998 paper by Andrew Wakefield, which has been thoroughly retracted and exposed as scientific misconduct, yet continues to resurface in modified forms to fit contemporary conspiracy theories. Other recurring falsehoods include exaggerated claims about severe allergic reactions, fears regarding aluminum adjuvants and thimerosal (which is not used in the MMR vaccine), and unfounded assertions that natural infection is somehow safer than vaccination—a claim contradicted by the fact that measles can cause fatal complications like pneumonia and encephalitis. Health officials expressed particular frustration with the influence of anti-vaccine influencers and “health freedom” advocates who have successfully weaponized legitimate concerns about bodily autonomy and medical choice to promote a wholly unscientific agenda. Furthermore, the proliferation of misinformation has been exacerbated by the algorithmic amplification on platforms like Facebook, YouTube, and TikTok, where sensationalized content regarding vaccine injuries generates significantly higher engagement than factual, peer-reviewed data. The Jackson County Health Department has responded by launching a “Vaccine Truth” campaign, hosting town halls and partnering with local pediatricians to provide rebuttal narratives; however, officials acknowledge that reversing the cognitive damage of sustained misinformation is akin to turning around an ocean liner, requiring sustained community engagement and grassroots trust-building efforts.
Paragraph 4: Public Health Response, Contact Tracing, and Quarantine Protocols
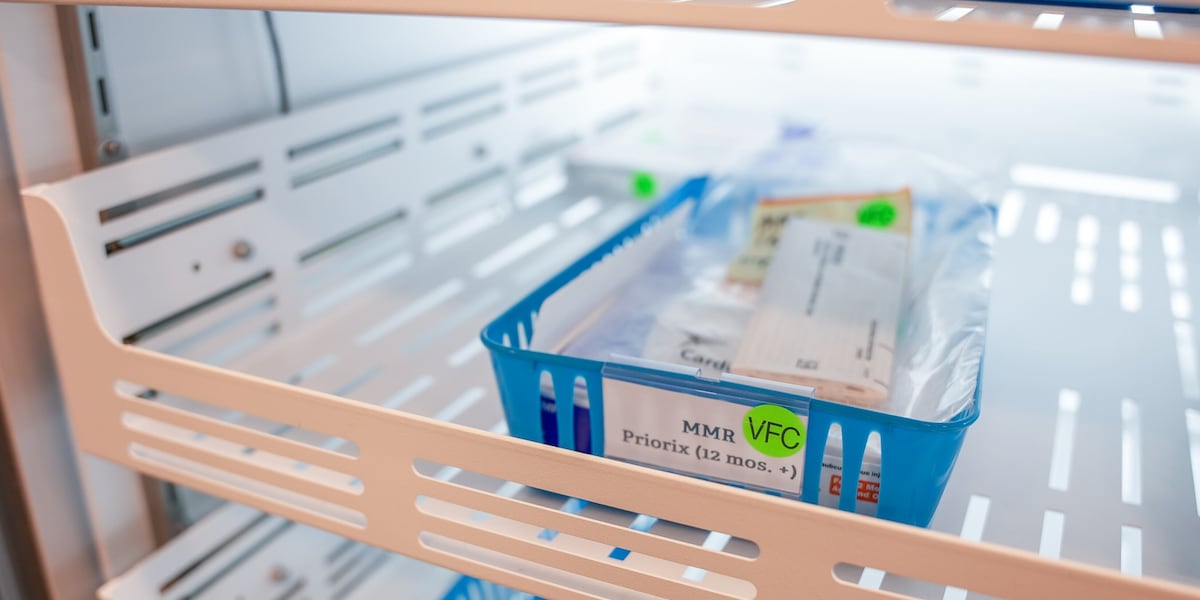
In the wake of the confirmed measles diagnosis, the Jackson County Public Health Department has activated its Emergency Operations Center and launched a comprehensive contact tracing initiative to map the potential exposure network. A dedicated team of disease investigators is working around the clock, interviewing the patient to construct a detailed itinerary of movements over the past two weeks, cross-referencing credit card transactions, and utilizing public surveillance footage where available. The primary focus is on identifying susceptible contacts—individuals who are unvaccinated or under-vaccinated—and placing them under a 21-day quarantine observation period, which corresponds to the maximum incubation period for the measles virus. Health officials have set up temporary vaccination clinics across the county, offering the MMR vaccine free of charge to any individual who has not completed their two-dose series, emphasizing the “post-exposure prophylaxis” window wherein vaccination within 72 hours of exposure can provide significant protection or mitigate symptom severity. Those who are unable to receive the vaccine, such as pregnant women or infants, are being advised to receive immunoglobulin therapy if exposed. Concurrently, the health department has issued a community-wide advisory warning residents to monitor for symptoms, which typically manifest 7 to 14 days post-exposure, and to contact healthcare providers before visiting emergency rooms to avoid further spread within medical facilities. Hospitals in the region are implementing stricter triage protocols, including placing anyone presenting with febrile rash illnesses into negative-pressure isolation rooms immediately, regardless of vaccination status. The economic and logistical cost of this response is substantial, diverting resources away from other routine public health programs, yet officials stress that the alternative—an unchecked outbreak—would be infinitely more burdensome, potentially overwhelming pediatric intensive care units and leading to avoidable fatalities.
Paragraph 5: Clinical Severity and The Overlooked Dangers of Measles
Amidst the logistical chaos of the public health response, medical professionals are taking the opportunity to re-educate the public on the true clinical severity of measles, a disease often incorrectly dismissed as a benign childhood rite of passage. While the initial symptoms—malaise, fever, and rash—may seem manageable, measles is a profoundly immunosuppressive illness. The virus infects and destroys memory cells in the immune system, creating a state of “immune amnesia” that can erase an individual’s prior immunity to other pathogens, leaving them vulnerable to bacterial superinfections like pneumonia, otitis media, and severe diarrhea for months or even years following recovery. Furthermore, roughly 1 in 1,000 infected children will develop encephalitis, an inflammation of the brain that can lead to permanent neurological damage, including seizures, deafness, and intellectual disability. The most devastating complication, however, is subacute sclerosing panencephalitis (SSPE), a rare but invariably fatal degenerative disease of the central nervous system that typically develops 7 to 10 years after the initial measles infection, even in individuals who had seemingly recovered completely. In the immediate crash course on measles pathology provided to the media, doctors highlighted that 1 in 5 infected individuals will require hospitalization, and the disease is particularly dangerous for children under five, adults over twenty, and immunosuppressed patients. Because the virus is airborne and highly aerosolized, standard handwashing and surgical masks offer insufficient protection; only N95 respirators or full vaccination provide reliable defense. Health officials worry that the public’s collective memory of measles severity has faded since its elimination, leading to a dangerous complacency amplified by misinformation, which tragically positions this current case as an educational opportunity for the community to relearn why this virus was targeted for eradication in the first place.
Paragraph 6: Official Statements, Community Call to Action, and Future Outlook
In a somber press conference concluding the initial response briefing, the Jackson County Health Department Director delivered a stirring address to the community, framing the current measles case not as a lone statistical anomaly but as a wake-up call regarding the fragility of public health infrastructure in the face of intentional ignorance. She specifically cited the confirmation of the case as direct evidence that “misinformation has consequences,” noting that her department is now spending vital hours on this outbreak that could have been otherwise spent on chronic disease prevention, maternal health, and other pressing health equity initiatives. The Director, alongside the county’s pediatric society and school superintendents, issued a unified call to action urging parents to review their children’s vaccination records and schedule catch-up doses immediately, offering weekend clinics and school-based vaccination drives to maximize accessibility. They also appealed directly to community leaders, faith-based organizations, and local influencers to assist in amplifying scientifically accurate information and to actively push back against the anti-vaccine narratives that have permeated social circles. Looking ahead, health officials anticipate that the coming two to three weeks will be critical in determining whether this single case remains an isolated incident or escalates into a sustained local outbreak. They plan to monitor absenteeism in schools and respiratory infection patterns closely, with contingency plans in place to declare a public health emergency should secondary transmission occur. The long-term outlook is cautiously optimistic but markedly uncertain; while the emergency response has been swift, the underlying issue of vaccine hesitancy remains unresolved. Officials have announced a multi-year community education grant proposal aimed at embedding vaccination literacy into school curricula and primary care workflows, recognizing that beating back the entrenched misinformation requires a sustained, generational effort. Ultimately, the message to Jackson County residents is clear: the safety of the community rests in the collective decision to trust scientific consensus over viral falsehoods, and the time to act is now, before the window of prevention closes.


